Medicare Basics
Medicare covers almost one in five Connecticut residents, just behind Medicaid’s enrollment. Medicare mainly covers seniors and people with disabilities. Only citizens and some legal residents can enroll in Medicare. Medicare offers good quality care, and almost all hospitals, doctors and other providers participate in the program.
Medicare is financed by taxes and payroll deductions from current workers, in addition to beneficiary premiums. Per person Medicare costs in Connecticut are far higher and growing faster than other coverage. Because the number of working Americans paying into the Medicare fund is declining while Medicare enrollment is climbing as Americans age, the program is facing a serious future financial crisis.
Medicare is different from Medicaid in that it covers mainly seniors and people with disabilities, has no income limit for eligibility, has costs for most members, does not cover all services, and is run entirely by the federal government. Also, unlike Medicaid, Medicare coverage and services are not free for most beneficiaries, averaging thousands of dollars per year per person. However, the two programs overlap. In 2025, just over one in six (67,149) Connecticut Medicare enrollees had household incomes that also qualified for full Medicaid coverage, termed Medicare-Medicaid enrollees or dual eligibles.
Medicare members have a choice of traditional coverage operated by the federal government or through a private Medicare Advantage insurer. Over half of Connecticut members have chosen to enroll in a Medicare Advantage plan. These plans offer all the services covered by traditional Medicare, in addition to some extra services. However, unlike traditional Medicare coverage, Medicare Advantage plans require burdensome prior authorizations for services, limit the providers patients can see, and use Artificial Intelligence (AI) to deny patients needed care. Medicare Advantage plans exaggerate patients’ health conditions and attract healthier patients to boost profits resulting in over $30 billion in overpayments.
Medicare Deeper Dive
How is Medicare different from Medicaid?
Both Medicare and Medicaid programs are run by government with public accountability. But there are important differences between the programs.
Medicare | Medicaid |
| Run by federal government | Run by state governments |
| Funded by federal government | Funded jointly by states and federal government |
| Covers seniors, people with disabilities | Covers children, parents, low-income seniors, people with disabilities, and low-income adults without children |
| No income limits | Income qualifications |
| Coverage set by federal government | Coverage set by state government |
In 2025, just over one in six (67,149) Connecticut Medicare enrollees had household incomes that also qualified for full Medicaid coverage, termed Medicare-Medicaid enrollees or dual eligibles.
Who does Medicare cover?
In 2024, Medicare covered almost 67 million (20%) Americans and 742,808 (also 20%) Connecticut residents. Medicare covers Americans over age 65 and people with long-term disabilities. Most people over age 65 qualify for Medicare, which is why less than one percent (0.7%) of Connecticut seniors are uninsured, compared to 5.6% of all state residents.
Medicare covers a wide range of services, but not dental, hearing, or vision care. Only citizens and lawfully present immigrants are eligible for Medicare. Undocumented immigrants pay into the program but are barred from Medicare coverage.
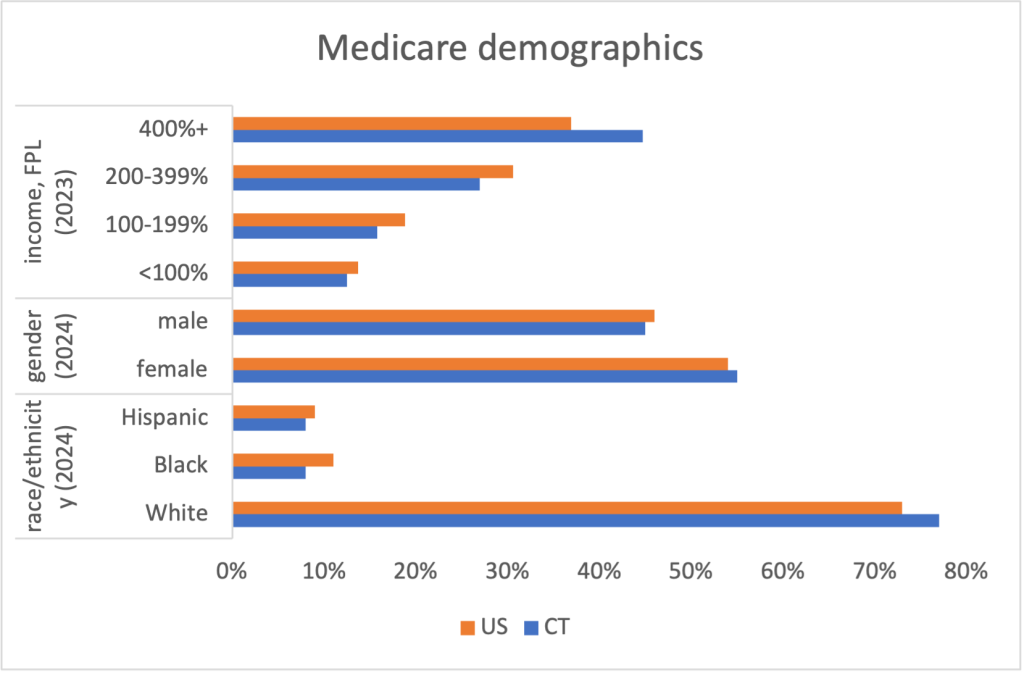
Seniors make up 91% of Connecticut Medicare’s enrollment and people with disabilities are 9%. While Americans at any income level qualify for Medicare, 28% of Connecticut beneficiaries have incomes at or below 200% of the federal poverty level, compared to 33% of all Americans covered by Medicare. Beneficiaries are more likely to be white and female both in Connecticut and the nation.
What services does Medicare cover and what does it cost?
In 2022, Medicare households spent twice as much of their budget on healthcare than other American households, leaving less room for housing, food, food, transportation, and other needs. It’s important to note that there is financial assistance for lower income Medicare beneficiaries. Connecticut’s Medigap and assistance programs are national models.
Medicare coverage is structured in separate parts that cover different services and are funded differently. Traditional Medicare does not cover dental, hearing or vision care. Inpatient and nursing home care is limited. Traditional Medicare does not require prior authorization, except in very limited circumstances. Medicare Advantage plans, an option for beneficiaries, may cover limited extra services but come with more costs and restrictions on care.
| Medicare Parts | Coverage, costs to beneficiaries (2025) Source: What Does Medicare Cost?, Medicare.gov Financial assistance with costs is available |
| Part A | Covers: some inpatient hospital, some skilled nursing facility, some home health, hospice Costs: Most people have no monthly premiums for Part A $1,676 annual deductible |
| Part B | Covers: Outpatient care including physician services, tests, outpatient surgery, some home health, durable medical equipment Part B coverage is voluntary, but 95% of beneficiaries enroll Costs: Monthly premiums of $185.00, more for people with higher incomes Premiums are deducted from Social Security checks $257 annual deductible, then patients pay 20% of the costs of care |
| Part C | Medicare Advantage — private managed care plans See section below |
| Part D | Covers: Prescription drugs Provided through private insurance plans See section below |
How much do drugs cost in Medicare?
Part D was added to Medicare in 2006 to cover the costs of prescription drugs for those who don’t have coverage through a retiree plan, a Medicare Advantage Plan, or Medicaid. Part D coverage is voluntary; however, penalties may apply for delaying enrollment. Enrollment in Part D plans has slowed while enrollment in Medicare Advantage Plans, which cover drugs along with medical services, has grown.
Enrollees must purchase Part D coverage through private insurance plans. In 2022 Connecticut Medicare enrollees had a choice among 14 Part D plans with monthly premiums that average $48.56. Not all plans are available in all areas of Connecticut. Enrollees should contact the state’s Choices program to find the best plan that works for them.
Until passage of the Inflation Reduction Act in 2022, by law Medicare paid the high list prices for prescription drugs. In contrast, private insurers can negotiate lower prices with drug companies resulting in significant savings. Under the new law, Medicare was directed to begin negotiating prices for drugs with the highest total spending. The first set of lower prices will be effective January 1, 2026. Starting in 2023, the law also required drug companies to limit increases in drug prices to the level of general inflation. If drug prices rise too much, the companies must refund the difference back to beneficiaries and the government. In December 2023, makers of 48 drugs with price increases above inflation were required to pay rebates that saved beneficiaries between $1 and $2,766 per dose. Together, the two provisions are expected to save Medicare $25 billion annually by 2031. Repeated lawsuits by drug companies challenging Medicare drug price negotiation have been unsuccessful.
What are Medicare Advantage plans?
Called Medicare Part C and established in 1997, private insurance Medicare Advantage plans usually offer lower patient costs, lower premiums, and limited extra benefits such as dental, hearing, and vision care. Medicare Advantage plans are required to cover all the services covered in traditional Medicare. Enrollment in Part C is voluntary for members growing. In 2024, over half (56%) of Connecticut Medicare beneficiaries were enrolled in Medicare Advantage plans. Enrollment in a Medicare Advantage plan is voluntary for members; they can switch in or out of plans annually.

Three quarters of Medicare Advantage members pay no premiums for care beyond prescription coverage. But Medicare Advantage plans usually require prior authorization for services, restrict care to providers in their network, and require referrals to see a specialist. Traditional Medicare covers care provided by any participating provider and does not require referrals or prior authorization. All Connecticut hospitals and 98% of doctors accept traditional Medicare patients.
In 2024, over half (56%) of Connecticut Medicare beneficiaries were enrolled in Medicare Advantage plans. The average 2025 Medicare Advantage monthly premium for Connecticut members is $20.03 but some plans have no premium. Members can choose among 41 plan options.
Most Medicare Advantage members are satisfied with their plan. Patients can save a good amount of money in Medicare Advantage, if they stay healthy. Medicare Advantage plan premiums are lower than traditional Medicare and declining, and the plans may offer limited extra services.
Unlike traditional Medicare, nearly all Medicare Advantage plans require prior authorization for many services. Under prior authorization, enrollees must get approval from their insurer before getting a service. If prior authorization is denied, the service is unlikely to be covered. Thirteen percent of Medicare Advantage members have had a prior authorization or claim denied. Half of Medicare enrollees would spend more for a 5-day hospital stay in a Medicare Advantage plan than in traditional Medicare. Due to prior authorization and slow payments, many hospitals are dropping out of Medicare Advantage plans. A US Senate investigation found that Medicare Advantage plans also use Artificial Intelligence (AI) technologies to deny patients needed care.
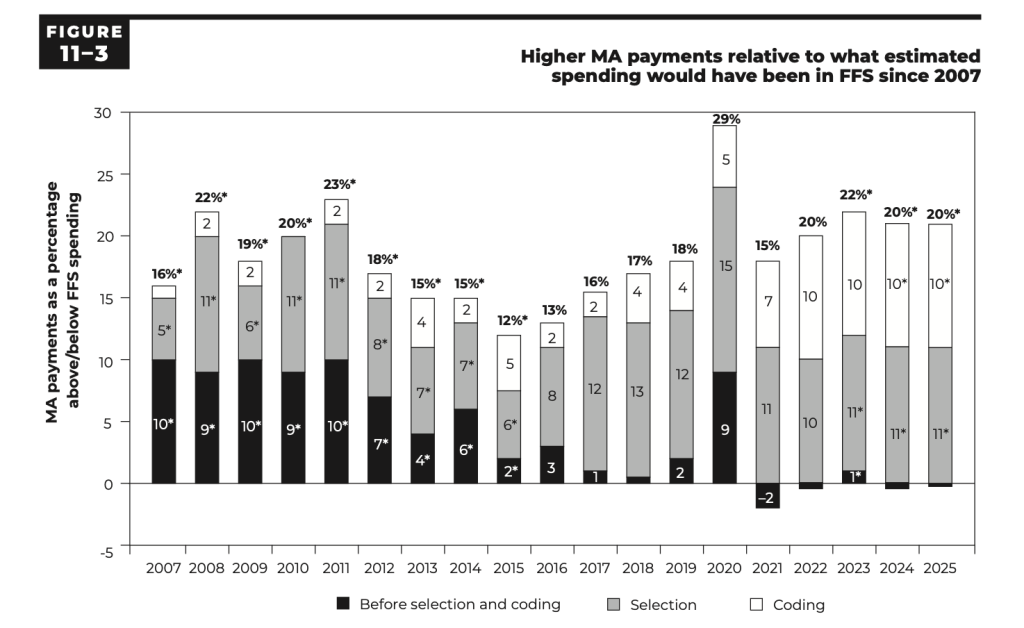
In a complicated process, Medicare Advantage plans are paid a set monthly fee per member, also called capitation, by the federal government to cover all healthcare costs, regardless of how much care members get. Historically, Medicare Advantage plans have attracted healthier members and lowered their medical costs to boost profits. Medicare Advantage plans also have a history of inappropriate upcoding, exaggerating the health problems of their members to get over $30 billion in higher payments from Medicare.
What are Medigap supplemental plans?
Medigap, or Medicare Supplemental Insurance, plans are offered by private insurers to supplement traditional Medicare costs. Unlike Medicare Advantage plans, Medigap plans do not make coverage decisions, limit the providers enrollees can use, or require prior authorization. Medigap plans cover some or all of enrollee’s put-of-pocket costs such as deductibles, copays, and coinsurance. The plans are standardized, labelled by letters A through N, making it easier to compare coverage. Connecticut Medigap premiums for 2025 range from $48 to $1,209.10 monthly depending on coverage and eligibility.
Connecticut’s Medigap and financial assistance programs are national models.
Is Medicare good coverage?
The large majority of Medicare beneficiaries are satisfied with their coverage (92%), higher than private insurance satisfaction levels. Medicare enrollees are less likely to report difficulty with their coverage than Americans with any other source of coverage. Among Medicare beneficiaries, people with disabilities are more likely than seniors to report problems.
Only 1.5% of Connecticut physicians opt-ed out of Medicare in 2024, similar to our surrounding states. Despite lower payment rates than private insurance, most Connecticut physicians accepted new Medicare patients in 2019 (84%). However, that rate was below the US average (89%) and our surrounding states. Nine in ten (91%) Connecticut physicians accepted new commercial plan patients.

Medicare and Medicare Advantage plans perform about evenly in quality. Beneficiaries in both programs experience similar wait times for appointments, adequacy of available providers, and care coordination.
Who runs Medicare?
Medicare is run by the federal government under the Centers for Medicare and Medicaid Services (CMS). It is essentially the same program across the US. CMS, following laws passed by Congress, decides what services are covered for Medicare enrollees, the rates providers in traditional Medicare are paid, and what Medicare Advantage plans are paid to provide all Medicare services for their enrollees.
How much does traditional Medicare pay providers?
Medicare pays hospitals per discharge rates based on patient diagnosis, adjusted for the severity of patients’ conditions. Physician payments in traditional Medicare are based on the effort required and costs of providing each service to patients, adjusted for some provider expenses and geographic location. Physicians can also earn bonuses for better quality care. Non-physician providers, including nurse practitioners, are usually paid 15% less.
In contrast, commercial plan payment rates for providers are based on negotiation, rather than set prices. Commercial plan prices for both hospitals and physicians closely track with providers’ market power. There is no evidence that hospitals and providers negotiate higher payment rates from commercial plans to cover lower Medicare and Medicaid rates.
Prices paid by Medicare for hospital services are about half what commercial plans pay for the same services. Commercial plan payment rates also vary considerably between payers and geographic areas, while traditional Medicare rates are consistent. Commercial plans pay about 29% higher rates for physician services than Medicare does. Connecticut commercial plan payment rates for both hospitals and physicians are relatively generous compared to other states, while Medicare payment rates for physicians in Connecticut are similar to the rest of the US.
How is Medicare funded?
Medicare is funded by payroll taxes taken from American’s paychecks, by premiums charged to enrollees, and by the federal budget. Undocumented immigrant workers pay into the program but are prohibited from coverage under Medicare.
Medicare spending has grown significantly over the years to $1 trillion in 2023 and it is expected to double in the next decade. This increase is driven by more Americans reaching age 65 and living longer, rising prices for drugs, healthcare consolidation driving up prices for services, and rising utilization of services.

Connecticut per person spending on Medicare was both higher and grew much faster than other payers from 2022 to 2023, according to the 2025 report by the Office of Health Strategy.

Overpayments to Medicare Advantage plans are a significant driver of increased Medicare spending. According to MedPAC, the overpayments result from plans exaggerating patient healthcare problems, while in fact, attracting healthier members than traditional Medicare. As Medicare Advantage enrollment grows, total spending will rise. It is estimated that Medicare Advantage overpayments will cost an extra $1.2 trillion over the next ten years.
Is Medicare going to run out of money? What happens then?
For decades, experts have warned of a massive, unsustainable jump in Medicare spending. But it hasn’t happened. The federal trust fund that covers hospital care in Medicare (Part A) is now scheduled to run out of money in 2036, but this date changes annually, usually to later years. In both 2011 and 2012, CMS predicted that the Trust Fund would have run out of money last year. The new date is a decade longer than the estimate from before the COVID pandemic.
However, there are valid concerns about the solvency of the program. Medicare’s Hospital Insurance Trust Fund pays for Medicare Part A costs such as inpatient hospital, skilled nursing facility, some home healthcare, and hospice bills. As the nation’s population ages, more Americans are relying on Medicare for coverage. At the same time, the number of active workers paying into the Trust Fund through their paychecks is declining. Healthcare prices are rising faster than the wages of workers paying into the funds, which amplifies the deficit.
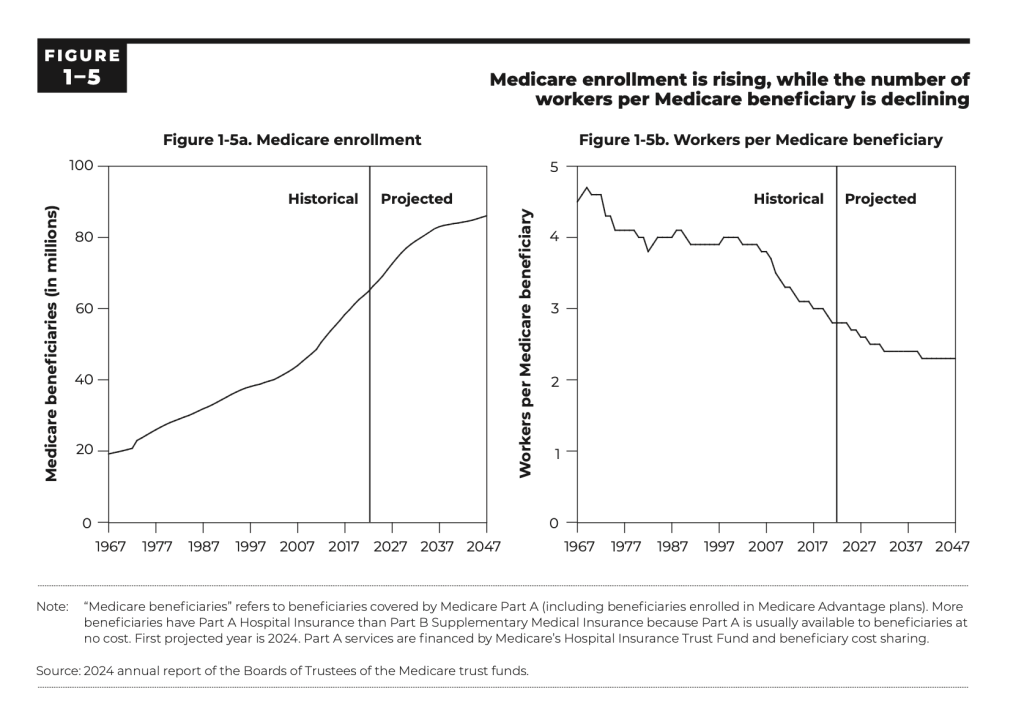
If the Trust Fund is allowed to empty, Medicare hospital bills would be paid but only up to the level of payroll taxes coming into the fund. It’s important to note that Congress has never allowed the Trust Fund to become depleted.
It’s also important to note that payments for Parts B and D – outpatient and drug coverage – are funded by premiums and federal taxes, so they are not dependent on the Hospital Trust Fund. Premiums and federal tax funding for Parts B and D are set each year to cover the costs of the program.
Where does the money go?
Medicare covers a large and growing share of US healthcare bills. It is an especially important source of payments for home healthcare and drugs. (2022)

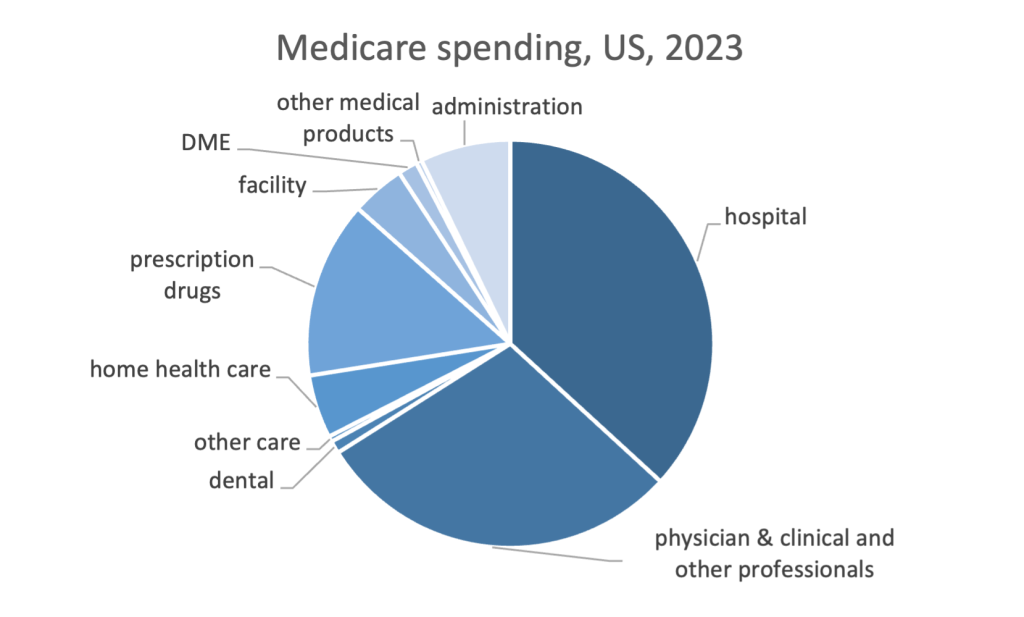
Medicare spending covers a variety of services. In 2023, the largest and fastest growing shares were spent on hospitals, clinical care, and prescription drugs.
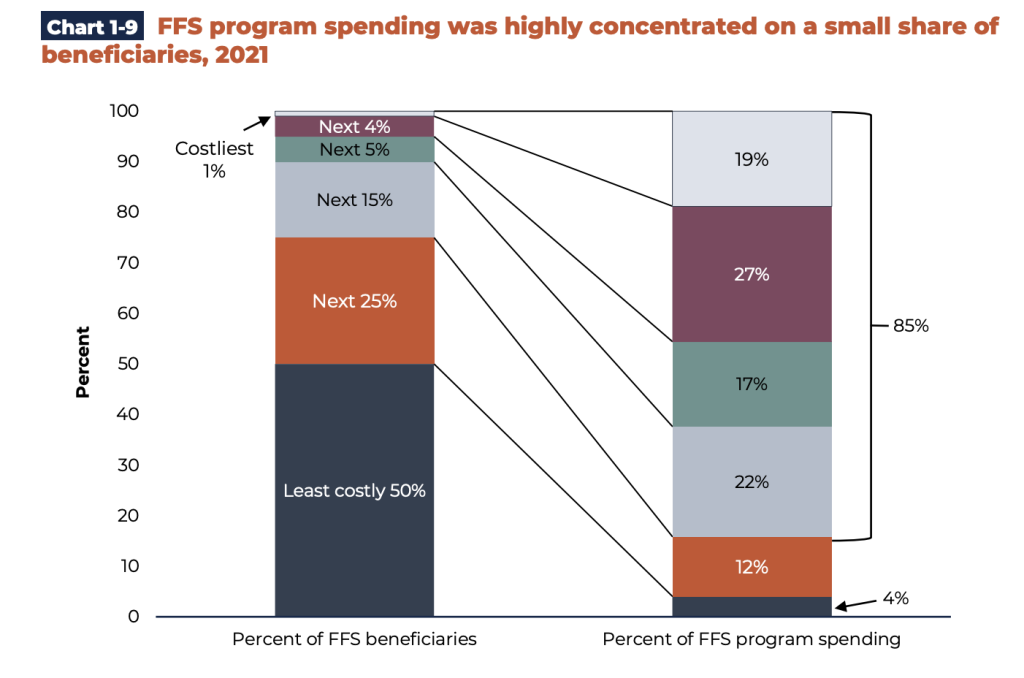
As for Medicaid and private insurance, spending is not evenly distributed between Medicare beneficiaries. A quarter of beneficiaries account for 85% of spending. This makes sense, as few individuals could cover the cost of a major health problem. Because Medicare is a large program, costs are spread over a large pool of people.
How does care work for people on both Medicare and Medicaid?
In 2025, just over one in six (67,149) Connecticut Medicare enrollees have household incomes that also qualify for full Medicaid coverage, termed Medicare-Medicaid enrollees or dual eligibles. Connecticut’s rate, at 17% of total Medicaid enrollment, was the sixth highest among states. In 2021, care for dual eligibles accounted for 35% of Connecticut Medicaid’s total budget, higher than the US average of 29%.
Medicaid pays some or all of the Medicare premiums and cost sharing for dually eligible members, depending on income. For lower income members, Connecticut covers all Medicaid services and costs not covered by Medicare, including dental, vision, home and community-based services, and mental health. Total costs of care are considerably higher for dual eligibles than for other enrollees. In 2021 nationally, Medicare spent $312 billion on dually eligible enrollees’ care while state Medicaid programs spent $181.5 billion. Higher costs for duals are driven by long-term services and supports spending, including institutional and home-based care.
How will the new federal budget bill affect Connecticut Medicaid?
In contrast to Medicaid, the Trump administration has proposed more modest changes to Medicare, as of August 2025.
- The new administration plans to lower prescription drug prices for beneficiaries and for the Medicare program. To date, plans include price transparency and expanding Medicare’s ability to negotiate drug prices. The administration reduced funding for a program that had reduced Part D insurance premiums, likely adding to rising costs for beneficiaries.
- The administration approach to Medicare Advantage is evolving. CMS has increased payments to Medicare Advantage plans but also approved a Biden administration regulatory proposal to reduce upcoding – the plans’ practice of exaggerating patients’ health conditions to boost profits and expanded plan audits for waste, fraud and abuse.
- The President reversed a policy to promote competition and enforce anti-trust laws. This is likely to enable more market consolidation which has led to higher healthcare prices and reduced consumer choice.
- CMS has increased Medicare physician payment rates to reflect inflation.
- The administration has made significant cuts to the agencies that operate Medicare, raising concerns about the ability to operate the program.
- The federal budget bill delays adoption of minimum staffing standards for long term care facilities for ten years.
Trends
- Enrollment is expected to continue to rise as the average age of the US population increases and seniors live longer.
- The growth of Medicare Advantage has slowed. Efforts to lower excessive costs and hold insurers accountable are also unclear.
- Congress needs to address the deficit in the Hospital Trust Fund to ensure Medicare’s sustainability.
Updated August 27, 2025
Many thanks to Kathy Holt, CT Healthcare Advocate, for critical feedback